
To read the full review go to Semi-recumbent position for the prevention of ventilator-associated pneumonia in adults requiring mechanical ventilation
Key messages
- For adults on breathing machines (ventilators) in an intensive care unit (ICU), raising the head of the bed to about a 30° to 45° angle instead of lying flat probably reduces lung infections and may shorten the time patients need a ventilator, without changes in death rates during the ICU or overall hospital stay.
- Raising the head of the bed higher (40º to 45º versus 30º; or 30º to 45° versus less than 30º) probably lowers the risk of lung infection but increases the risk of bedsores. Adding side‐to‐side turning (rotation) to a raised head position probably gives extra benefits, including fewer lung infections and a shorter time on a ventilator, in the ICU and in hospital.
- More large, well‐designed trials are needed to determine the optimal bed angle and to assess the effects on survival and potential harms.
What is ventilator‐associated pneumonia?
Ventilator‐associated pneumonia is a lung infection that develops in patients who have been using a ventilator (a machine that helps with breathing) for more than 48 hours. It is associated with an increased risk of death, longer stay in the ICU and in hospital overall, and greater healthcare costs.
What is 'head‐end elevation' or a semi‐recumbent position?
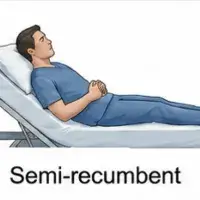
Head‐end elevation means raising the upper body rather than lying flat. The head of the bed is usually raised between 30° and 45°, although angles from 15° to 60° may be used. This is often called a 'semi‑recumbent' or 'semi‑upright' position.
There are also different types of semi‐recumbent positions with additional components; for example:
- semi‐recumbent lateral or lateral rotation position where patients are in a semi‐recumbent position and also rotated from side to side, either manually or continuously using a motorised turning bed; and
- semi‐recumbent rotation position where the head‐of‐bed angle is rotated through several different degrees (for example, 20º, then 30º, and then 45º).
What did we want to find out?
For ICU patients on ventilators, is raising the head of the bed (semi‐recumbent position) better than a flat bed and other bed positions for reducing:
- lung infections;
- death during the ICU stay or overall hospital stay;
- the length of stay in the ICU or hospital;
- the duration of assisted breathing through a ventilator; and
- bedsores?
What did we do?
We searched for studies that compared semi‐recumbent positioning with any other positioning, or different degrees or types of semi‐recumbent positioning, in ICU adult patients requiring a ventilator. We compared and summarised the results and assessed how confident we are in the findings, based on factors such as the study design and methods.
What did we find?
We found 48 studies involving 7955 patients in ICUs using ventilators. Thirty‐seven trials were conducted in China, two in Iran, and one each in Austria, France, India, Spain, Türkiye, the United Kingdom, and the Netherlands. Two studies were conducted across several high‐income countries. Participants were typically around 55 years old, and about one‐third were women. Study size ranged from 25 to 855 participants.
- Comparing head‐end elevation with flat position (17 studies with 2640 participants), raising the head of the bed reduces the risk of lung infections, and may also reduce the duration of assisted breathing through a ventilator, without changes in death rates during ICU stay or overall hospital stay. However, its impact on the length of ICU and hospital stay and bedsores remains uncertain.
- Comparing different levels of head‐end elevation (30º to 45° versus less than 30º; 11 studies with 1153 participants, or 40º to 45º versus 30º; 14 studies with 1374 participants), raising the head of the bed higher probably reduces the risk of lung infections, but increases the risk of bedsores. However, these positions may not make a difference in reducing the risk of death during the ICU stay or overall hospital stay. The effects on time spent in ICUs or hospitals, or how long the patient needs assisted breathing with a ventilator machine, remain uncertain.
- Compared to regular head‐end elevation (7 studies with 708 participants), adding side‐to‐side turning probably further reduces the risk of lung infections, and shortens the duration of assisted breathing through a ventilator, as well as the length of stay in both ICU and hospital.
- The effects of raising the head of the bed to a very high angle (60° versus 45°), or using other body positions, are unclear (for example, different rotational positions, positions where patients are lying face down on their stomach, or positions where the patient's feet are lifted to be higher than their head).
What are the limitations of the evidence?
Our confidence in the results is limited. Many studies did not report whether patients remained in their assigned positions, and some did not clearly define lung infections, making the findings less reliable and harder to apply in practice.
How up to date is this evidence?
This updates our previous version of the review, published in 2016. The evidence is current to 3 October 2025.